
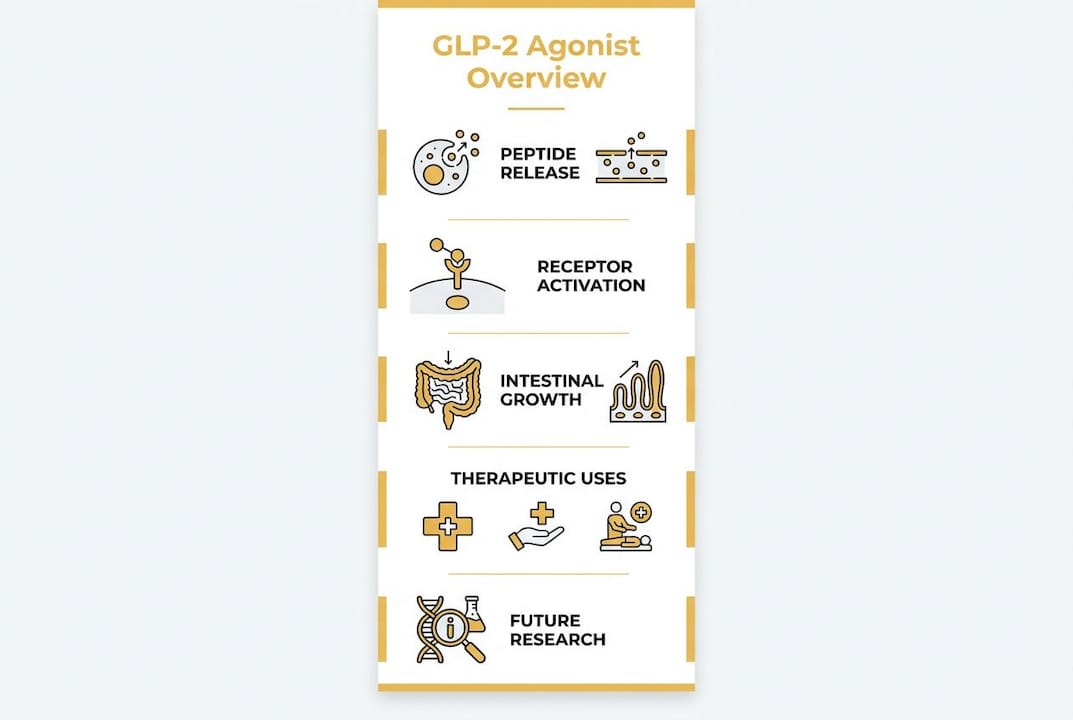
A GLP-2 agonist is defined as a synthetic peptide analog that activates the glucagon-like peptide-2 receptor (GLP-2R) to stimulate intestinal growth, repair mucosal architecture, and restore gut barrier function. The GLP-2 receptor, formally designated GLP-2R, is the sole confirmed target for this drug class, and its activation drives a cascade of intestinotrophic effects critical to gastrointestinal rehabilitation. Teduglutide, approved by the FDA under the brand name Gattex, remains the only fully approved GLP-2 agonist drug for short bowel syndrome (SBS) in adults and pediatric patients. Emerging agents including glepaglutide and apraglutide are advancing through phase 3 trials, while dual GLP-1/GLP-2 receptor agonists such as dapiglutide are expanding the therapeutic frontier into metabolic disease. Regulatory bodies including the FDA and the European Medicines Agency (EMA) have granted teduglutide orphan drug designation, reflecting both the severity of SBS and the limited treatment options available to this population.
How do GLP-2 agonists work? Mechanism of action and receptor biology
GLP-2 is a 33-amino-acid peptide secreted by intestinal L-cells in response to nutrient intake, and its native half-life is approximately 7 minutes before rapid degradation by dipeptidyl peptidase-4 (DPP-4). Teduglutide extends this to roughly 2 hours through an Ala²→Gly² amino acid substitution that confers DPP-4 resistance. That pharmacokinetic gain is what makes once-daily subcutaneous dosing clinically viable.
The GLP-2 receptor is absent on intestinal epithelial cells. Intestinotrophic effects occur entirely through paracrine signaling from subepithelial myofibroblasts and enteric neurons, which express GLP-2R and release downstream mediators. The two primary paracrine intermediates are IGF-1 and keratinocyte growth factor, both of which act on epithelial cells to drive crypt proliferation and villus elongation. This indirect mechanism distinguishes GLP-2R signaling from GLP-1R signaling, which acts directly on target cells in the pancreas and central nervous system.

Species differences in GLP-2R expression add a critical layer of complexity for translational research. Murine models demonstrate appetite regulation and pancreatic effects through GLP-2R activation that do not replicate in human subjects. Researchers designing preclinical studies must account for this divergence when interpreting rodent data and projecting efficacy in human trials.
| Receptor location | Signaling intermediates | Physiological outcome |
|---|---|---|
| Subepithelial myofibroblasts | IGF-1, keratinocyte growth factor | Crypt proliferation, villus elongation |
| Enteric neurons | Neuropeptide Y, vasoactive intestinal peptide | Gut motility modulation |
| Hepatic portal axis | Indirect metabolic signaling | Lipid absorption, glycogen synthesis |
| Hypothalamus (murine only) | Neuropeptide signaling | Appetite suppression (not confirmed in humans) |
Pro Tip: When designing GLP-2R studies using murine models, validate receptor distribution with species-specific immunohistochemistry before extrapolating functional data to human physiology. Murine GLP-2R expression in the hypothalamus and pancreas does not mirror human receptor localization.
What are the clinical applications of GLP-2 agonist therapy?
Teduglutide is the clinical benchmark for GLP-2 therapy, dosed at 0.05 mg/kg daily subcutaneously with dose adjustment required in renal impairment. Its primary indication is SBS in patients dependent on parenteral nutrition (PN), where it reduces PN volume and frequency by enhancing intestinal absorption capacity. The clinical significance is substantial: reducing PN dependency lowers infection risk, improves quality of life, and decreases long-term healthcare costs.
The cost profile of teduglutide is a defining clinical reality. Annual costs exceed $300,000 for adult patients, placing it among the most expensive chronic therapies in gastroenterology. That cost burden shapes prescribing decisions and underscores the need for next-generation agents with improved pharmacoeconomic profiles.
New long-acting analogs including glepaglutide and apraglutide are in phase 3 trials and may offer weekly dosing intervals, which would meaningfully improve adherence. Glepaglutide has also demonstrated anti-inflammatory and mucosal regenerative effects in experimental colitis models, suggesting potential utility beyond SBS in inflammatory bowel disease (IBD) and gut barrier restoration.
Clinical benefits of GLP-2 agonist therapy:
- Reduction in parenteral nutrition volume and infusion frequency in SBS
- Increased intestinal villus height and crypt depth, improving absorptive surface area
- Enhanced gut barrier integrity, reducing bacterial translocation risk
- Anti-inflammatory effects on intestinal mucosa in preclinical IBD models
- Potential reduction in SBS-associated liver disease linked to prolonged PN
Common side effects and monitoring requirements:
- Abdominal pain, nausea, and injection site reactions (most frequent)
- Fluid retention and peripheral edema, particularly in the first weeks of therapy
- Baseline colonoscopy required before teduglutide initiation
- Annual colonoscopy surveillance recommended during long-term treatment
- Dose reduction required in patients with moderate to severe renal impairment
The GLP-2 era represents a shift from supportive nutrition management toward active intestinal rehabilitation with regenerative pharmacology. That conceptual shift carries real clinical weight: clinicians are now expected to think about intestinal adaptation as a modifiable biological process, not a fixed outcome.
What are dual GLP-1/GLP-2 receptor agonists and their metabolic effects?
Dual GLP-1/GLP-2 receptor agonists represent the next generation of incretin-based therapy, designed to activate both receptor subtypes simultaneously for synergistic metabolic and intestinal benefit. Dapiglutide is the most advanced agent in this class, currently in phase 3 development. The mechanistic rationale is direct: GLP-1R activation drives insulin secretion, appetite suppression, and weight reduction, while GLP-2R activation supports beta-cell health without triggering acute insulin release, and simultaneously promotes intestinal growth.
The GLP-2 receptor functions as an integrative hub in the gut-brain-liver axis, influencing metabolism and nutrient partitioning beyond its intestinotrophic role. Dual agonism therefore targets metabolic homeostasis at multiple levels simultaneously. This is a meaningful departure from monotherapy GLP-1 receptor agonists, which do not address intestinal morphology or mucosal repair.
| Feature | GLP-1R agonist | GLP-2R agonist | Dual GLP-1R/GLP-2R agonist |
|---|---|---|---|
| Primary target | Pancreas, CNS | Intestinal myofibroblasts, neurons | Both |
| Insulin secretion | Stimulates | No direct effect | Stimulates |
| Intestinal growth | Minimal | Strong trophic effect | Strong trophic effect |
| Appetite regulation | Suppresses | Minimal (humans) | Suppresses |
| Weight reduction | Established | Not primary | Anticipated |
| Beta-cell support | Indirect | Direct (GLP-2R mediated) | Combined |
| Development stage | Approved (multiple agents) | Approved (teduglutide) | Phase 3 (dapiglutide) |
Dual agonists are particularly relevant for researchers studying the intersection of metabolic disease and gastrointestinal pathology. Conditions such as obesity-associated intestinal permeability and type 2 diabetes with gut dysmotility represent plausible indications where combined receptor activation could deliver outcomes neither monotherapy achieves alone.
Safety challenges and future directions in GLP-2 research
The trophic properties of GLP-2R agonists that make them therapeutically valuable also generate their most significant safety concern. Chronic stimulation of intestinal proliferation carries a theoretical risk of promoting mucosal neoplasia, particularly in patients with pre-existing dysplasia or IBD-associated mucosal changes. This risk is not merely theoretical in the context of IBD: subepithelial myofibroblasts implicated in fibrosis and stricturing complications in Crohn’s disease are the same cells that express GLP-2R and mediate its trophic effects.
Patient stratification is therefore not optional. It is the defining clinical challenge for expanding GLP-2 therapy beyond SBS into IBD and other gastrointestinal indications. Researchers and clinicians must distinguish between luminal inflammatory phenotypes where mucosal regeneration is beneficial and fibrostenosing phenotypes where GLP-2R stimulation could accelerate stricture formation.
Key safety and research priorities for GLP-2 agonist integration:
- Mandatory baseline and annual colonoscopy surveillance for all patients on long-term therapy
- Exclusion or careful monitoring of patients with active dysplasia or colorectal adenomas
- Phenotype-specific patient selection in IBD, prioritizing inflammatory over fibrostenosing disease
- Development of biomarkers to identify patients at elevated neoplasia risk before therapy initiation
- Formulation research targeting extended half-life and reduced injection frequency for adherence
Future directions in GLP-2 research include oral and inhaled peptide delivery systems, precision dosing guided by intestinal adaptation biomarkers, and combination protocols pairing GLP-2R agonists with mucosal healing agents. Expert meetings convened by the American Society for Parenteral and Enteral Nutrition (ASPEN) have highlighted the need for prospective registries to capture long-term safety data outside of controlled trial conditions.
Pro Tip: Prioritize mucosal surveillance protocols before initiating GLP-2 therapy in any patient with a history of IBD-associated dysplasia or colorectal polyps. The trophic benefit and the neoplasia risk originate from the same receptor pathway, making surveillance non-negotiable rather than precautionary.
Key Takeaways
GLP-2 agonists drive intestinal regeneration through paracrine GLP-2R signaling, and their clinical and research value depends entirely on precise patient selection and rigorous safety monitoring.
| Point | Details |
|---|---|
| Receptor biology is indirect | GLP-2R is absent on epithelial cells; all trophic effects occur via IGF-1 and keratinocyte growth factor from myofibroblasts. |
| Teduglutide sets the clinical standard | FDA-approved at 0.05 mg/kg daily, it reduces parenteral nutrition dependence in SBS with annual costs exceeding $300,000. |
| Dual agonists expand the scope | Dapiglutide targets both GLP-1R and GLP-2R, combining metabolic and intestinal benefits not achievable with monotherapy. |
| Safety surveillance is mandatory | Baseline and annual colonoscopy are required; fibrostenosing IBD phenotypes carry elevated risk from chronic GLP-2R stimulation. |
| Translational research requires caution | Murine GLP-2R expression in the hypothalamus and pancreas does not replicate in humans, limiting direct extrapolation. |
Why GLP-2 receptor biology deserves more attention than it gets
After years of following GLP-1 research dominate the metabolic pharmacology conversation, the GLP-2 receptor has consistently been treated as the quieter sibling. That framing is a mistake, and I think it has slowed clinical integration in ways that are now becoming apparent.
What strikes me most about GLP-2R biology is the elegance of its indirection. The receptor does not sit on the cells it ultimately transforms. It works through myofibroblasts and neurons, releasing IGF-1 and keratinocyte growth factor to reshape epithelial architecture from the outside. That paracrine design has profound implications for drug delivery research that most investigators have not fully acted on yet.
The translational gap between murine models and human physiology is the issue I find most underappreciated in the literature. Appetite regulation and pancreatic effects observed in rodents have generated hypotheses that simply do not hold in human trials. Researchers who build study designs around murine receptor distribution data without validating human expression patterns are setting themselves up for null results that could have been anticipated.
The dual agonist space is where I see the most genuine scientific excitement, and also the most risk of moving faster than the safety data supports. Dapiglutide’s phase 3 program will answer critical questions about whether combined GLP-1R and GLP-2R activation delivers additive benefit or introduces compounded risk in populations with metabolic and gastrointestinal comorbidities. The answer will define the next decade of incretin pharmacology.
— Kristian
Alphagenrx: Research-grade GLP-2 analogs for serious investigators
Researchers advancing GLP-2 receptor biology and intestinal rehabilitation science require compounds that meet the same standard as the questions they are asking. Alphagenrx supplies laboratory-grade research peptides including GLP-2 analogs and related compounds, backed by independent testing, verifiable documentation, and rigorous quality standards.
Every compound from Alphagenrx is supported by transparent sourcing and third-party verification, giving your laboratory the confidence to build reproducible protocols. Whether your work focuses on intestinal morphology, dual receptor agonism, or metabolic pathway research, Alphagenrx provides the precision your science demands. Visit Alphagenrx to review available research compounds and documentation.
FAQ
What is a GLP-2 agonist?
A GLP-2 agonist is a synthetic peptide that activates the GLP-2 receptor to stimulate intestinal growth, enhance mucosal repair, and improve gut barrier function. Teduglutide is the only FDA-approved agent in this class, indicated for short bowel syndrome.
How does the GLP-2 receptor mechanism differ from GLP-1?
GLP-2R is expressed on subepithelial myofibroblasts and enteric neurons rather than on epithelial cells directly, producing intestinotrophic effects through paracrine mediators including IGF-1 and keratinocyte growth factor. GLP-1R acts directly on pancreatic beta-cells and central nervous system targets.
What monitoring is required during long-term GLP-2 therapy?
Teduglutide requires a baseline colonoscopy before initiation and annual colonoscopy surveillance during treatment to monitor for mucosal dysplasia. Dose adjustment is also required in patients with moderate to severe renal impairment.
What are dual GLP-1/GLP-2 receptor agonists?
Dual GLP-1/GLP-2 receptor agonists such as dapiglutide activate both receptor subtypes simultaneously, combining the metabolic effects of GLP-1R activation with the intestinotrophic and beta-cell support effects of GLP-2R activation. Dapiglutide is currently in phase 3 clinical trials.
Can GLP-2 agonists be used in inflammatory bowel disease?
GLP-2 agonists show anti-inflammatory and mucosal regenerative effects in preclinical IBD models, but clinical use requires careful patient stratification. Fibrostenosing IBD phenotypes carry elevated risk because GLP-2R stimulation of subepithelial myofibroblasts may accelerate fibrosis and stricture formation.